
Enterprise Applications · Editable reference architecture
Telemedicine platform architecture
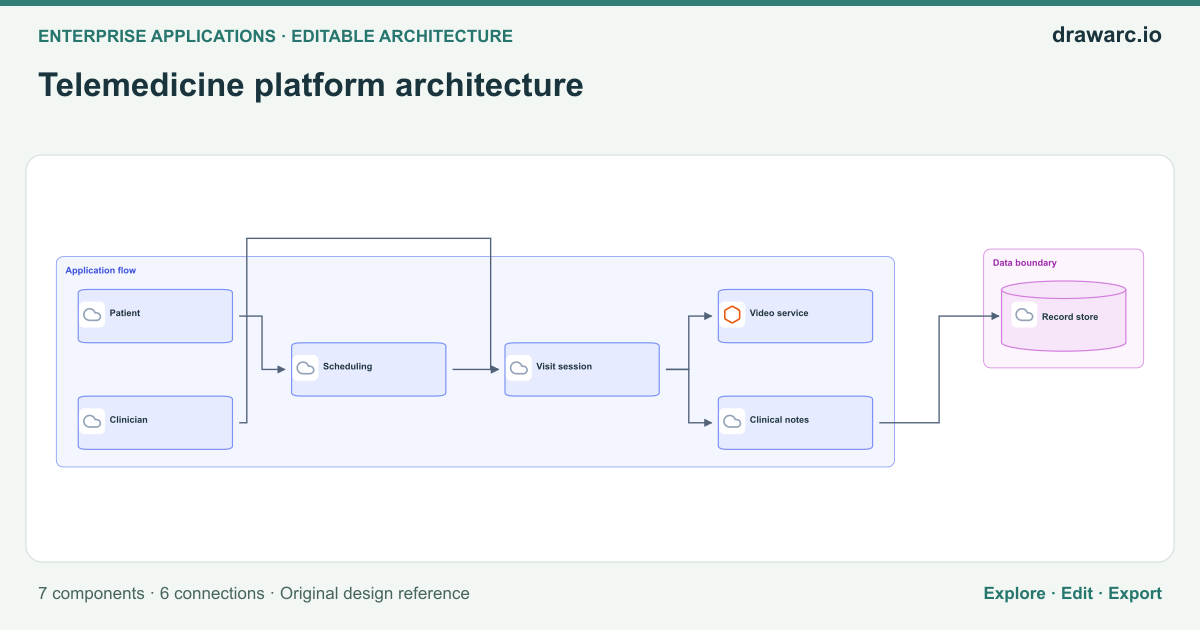
An editable telemedicine platform architecture reference showing Patient → Scheduling → Visit session and downstream dependencies. Protect media and clinical records independently.
Open & Edit in DrawArc (Free, No Login Required)Your changes stay in a separate draft on this browser. Download an editable project to keep a portable copy.
7 components · 6 connections · Open the editor to zoom, move nodes and edit source.
Architectural overview
Telemedicine platform architecture addresses the responsibilities and boundaries shown in this reference rather than prescribing an entire production deployment. The primary flow starts at Patient and reaches Video service through Scheduling, Visit session. Use this view to explain which component initiates work, which component owns a decision, and where a dependency can affect the caller. Protect media and clinical records independently.
The diagram contains 7 distinct components and 6 directed relationships. A separate path connects Clinician → Visit session → Clinical notes. A separate path connects Clinical notes → Record store. These arrows describe logical interactions; they do not establish authentication, network access, atomic transactions or delivery guarantees. Label the actual protocol, payload contract and owner when adapting the drawing to your system. Keep synchronous and asynchronous boundaries explicit so that a reviewer can identify where a request ends and a later operation begins.
Before implementing this architecture, define expected load, data classification, latency budgets and recovery objectives. Give Patient a bounded dependency timeout and a documented failure response. For Record store, specify ownership, retention, access control and a tested recovery procedure. Validate the decision above against your workload instead of treating the presence of a component as proof of reliability. Open the editable canvas, replace generic labels with real deployment units, and document the decisions that differ from this reference.
The real-world problem
Design or explain telemedicine platform architecture with explicit ownership and dependency paths. Protect media and clinical records independently.
Data flow
Connections from this diagram. Branches and control signals are not a single chronological sequence.
- Patient → Scheduling. Define the interaction contract and trace the resulting response or state change.
- Scheduling → Visit session. Define the interaction contract and trace the resulting response or state change.
- Visit session → Video service. Define the interaction contract and trace the resulting response or state change.
- Clinician → Visit session. Define the interaction contract and trace the resulting response or state change.
- Visit session → Clinical notes. Define the interaction contract and trace the resulting response or state change.
- Clinical notes → Record store. Define the interaction contract and trace the resulting response or state change.
Security boundaries
- Authenticate callers at the boundary before Scheduling accepts protected work; authorize the specific operation rather than trusting network placement.
- Use separate service identities and least-privilege permissions for Scheduling, Visit session, Video service. Encrypt sensitive traffic, protect credentials and avoid placing confidential payloads in logs.
- Restrict and audit access to Record store; define retention and deletion requirements for the actual data.
Failure handling
Patient is unavailable or slow
Response: Apply bounded timeouts and controlled backoff only where retrying is safe. Return an explicit failure or durable acceptance; do not report success before required work is committed.
Verify: Interrupt Patient in an isolated test and measure errors, recovery and any repeated side effects.
Record store loses or returns stale state
Response: Use workload-specific durability, reconciliation and tested recovery. Specify how stale reads or a failed write affect callers.
Verify: Exercise the failure path with representative records and verify both the visible response and the resulting state.
An invalid or incompatible input reaches Scheduling
Response: Validate the input contract before effects are committed. Preserve rejected input identifiers without exposing secrets, and document a safe replay or correction procedure.
Verify: Send malformed and older-version inputs through Patient and verify rejection, observability and unchanged valid state.
Trade-offs and alternatives
Protect media and clinical records independently.
- Benefit
- Makes the ownership and interaction boundaries visible for a focused design review.
- Cost
- The 7 illustrated components still require contracts, monitoring and operational ownership; extra boundaries can add latency and failure modes.
- Alternative
- Use a simpler deployment when it meets the same requirements, or split a boundary only after measuring a specific need.
Logical boundaries versus deployment units in Telemedicine platform architecture
- Benefit
- Keeps the responsibilities of Patient, Scheduling, Visit session visible without requiring a separate server for each box.
- Cost
- A logical view does not establish isolation, independent scaling or high availability; those require a separate deployment design and operational tests.
- Alternative
- Co-locate components in a simpler deployment first when ownership and workload requirements permit it.
When to use this architecture
- Explain telemedicine platform architecture to engineers or stakeholders using a concrete visual flow.
- Review this decision before deployment: Protect media and clinical records independently.
- Adapt a starting diagram for your own requirements, then record and validate every changed boundary.
Key components
- Patient
- Patient participates in telemedicine platform architecture. Patient → Scheduling. Define its contract, owner and access permissions in your implementation.
- Scheduling
- Scheduling participates in telemedicine platform architecture. Patient → Scheduling; Scheduling → Visit session. Define its contract, owner and access permissions in your implementation.
- Visit session
- Visit session participates in telemedicine platform architecture. Scheduling → Visit session; Visit session → Video service; Clinician → Visit session; Visit session → Clinical notes. Define its contract, owner and access permissions in your implementation.
- Video service
- Video service participates in telemedicine platform architecture. Visit session → Video service. Define its contract, owner and access permissions in your implementation.
- Clinician
- Clinician participates in telemedicine platform architecture. Clinician → Visit session. Define its contract, owner and access permissions in your implementation.
- Clinical notes
- Clinical notes participates in telemedicine platform architecture. Visit session → Clinical notes; Clinical notes → Record store. Define its contract, owner and access permissions in your implementation.
- Record store
- Record store participates in telemedicine platform architecture. Clinical notes → Record store. Define its contract, owner and access permissions in your implementation.
Questions about this template
What does this telemedicine platform architecture diagram show?
It shows 7 components with the core flow Patient → Scheduling → Visit session → Video service. Protect media and clinical records independently.
Can I edit this diagram without signing in?
Yes. Open the template in the browser-local canvas to change nodes, connections and source. AI generation and cloud account storage require sign-in.
Is this a complete production implementation?
No. It is an editable reference. Validate the security controls, dependency behavior, capacity and recovery plan against your own requirements before implementation.
Validate your implementation
Use the relevant platform documentation to verify service limits, supported features and configuration. This diagram is an original reference rather than a reproduction of a provider deployment.